
Open a routine clinical brain MRI in a DICOM viewer and flip to the coronal or sagittal plane, and the sharp axial series often turns into a stack of blurred bricks, because the protocol saved scan time by acquiring thick slices. Aditya Rastogi, Ramon Leiser, Philipp Vollmuth and colleagues from University Hospital Bonn, the German Cancer Research Center (DKFZ), Heidelberg University Hospital and University Medical Center Freiburg posted arXiv:2610.24858 on 17 October 2026 with a model called GSMR3D. It takes a low-resolution or thick-slice brain MRI volume and rebuilds it on any finer grid you ask for, with a separate scale factor per axis, using one trained model per MRI contrast. In their tests it kept small brain metastases detectable at slice spacings where plain interpolation loses a lot of them.
Why a viewer or PACS team should care
Every viewer that does multiplanar reformatting already “super-resolves” thick slices, usually with trilinear or cubic interpolation, and readers know what that looks like. The problem with learned super-resolution so far is that most models are trained for one geometry: one for isotropic 2x, another for 2x in-plane, another for 3 mm or 4 mm slices. A hospital archive holds all of those and more, with spacing that changes by scanner, sequence and site. A model that accepts whatever spacing the series has and returns a 1 mm grid is something you could run as one server-side step on incoming series, instead of keeping a zoo of models and routing rules. It would also sit in front of the segmentation and detection tools a viewer pipeline already runs, which work worse on thick slices.
What goes in and what comes out
The input is a 3D MRI volume at its acquired resolution, of any size, plus the target grid, given as a scale factor for each axis. Factors can be non-integer and different per axis, and training covered factors between 1x and 4x on each axis. The output is a volume on the target grid. Intensities are clipped to the 1st to 99.5th percentile and mapped to 0 to 1 before the model sees them, so the output is in normalized units, and a deployment would have to map it back before writing a series. There are two models in the paper, one for contrast-enhanced T1 and one for plain T1. Nothing else was trained, so T2, FLAIR or diffusion series would need their own model.
How it works
GSMR3D treats the low-resolution volume as samples of a continuous image that can be queried at any coordinate. An encoder runs once on the low-resolution grid. Its first layer is the frozen first block of NVIDIA’s MAISI 3D autoencoder, followed by twelve trainable residual blocks. For each low-resolution voxel, the network then picks shapes from a learned dictionary of 512 anisotropic 3D Gaussians. Anisotropic means a Gaussian can be long in one direction and short in another, which suits data that are fine in-plane and coarse between slices.
To compute one output voxel, the model looks only at the 3 x 3 x 3 neighbourhood of low-resolution voxels around it and weights their features with those Gaussians. The cost per output voxel stays fixed whatever the upscaling factor, so total runtime grows with the size of the output grid and nothing else. The gathered features are combined with a frequency encoding that knows the requested scale, decoded into a correction on top of trilinear interpolation, and refined. The idea borrows from Gaussian splatting, but instead of each Gaussian painting onto more and more output voxels as the grid gets finer, each output voxel gathers from a fixed set.
The last step is a measurement-consistency projection. The authors assume a known degradation, Gaussian blur followed by subsampling, and correct the output so that degrading it again gives back exactly the input volume. Whatever detail the network adds, it cannot change what the acquired data say under that assumption. This step needs no training and is solved with conjugate gradients at inference.
What the evaluation shows
The contrast-enhanced model was trained on about 3,700 volumes from the CENTRIC and CORE glioblastoma trials. The T1 model was trained mostly on about 30,000 volumes from the German National Cohort (NAKO) and then fine-tuned on the trial scans. Testing used 100 tumour patients from a separate trial (EORTC-26101), 100 healthy NAKO subjects and, as an external check, 100 brain-metastasis patients from the public MR-RATE dataset with 670 enhancing lesions. All low-resolution inputs were made from 1 mm scans by blurring and subsampling: isotropic 2x, in-plane 2x, and 3x and 4x thicker slices.
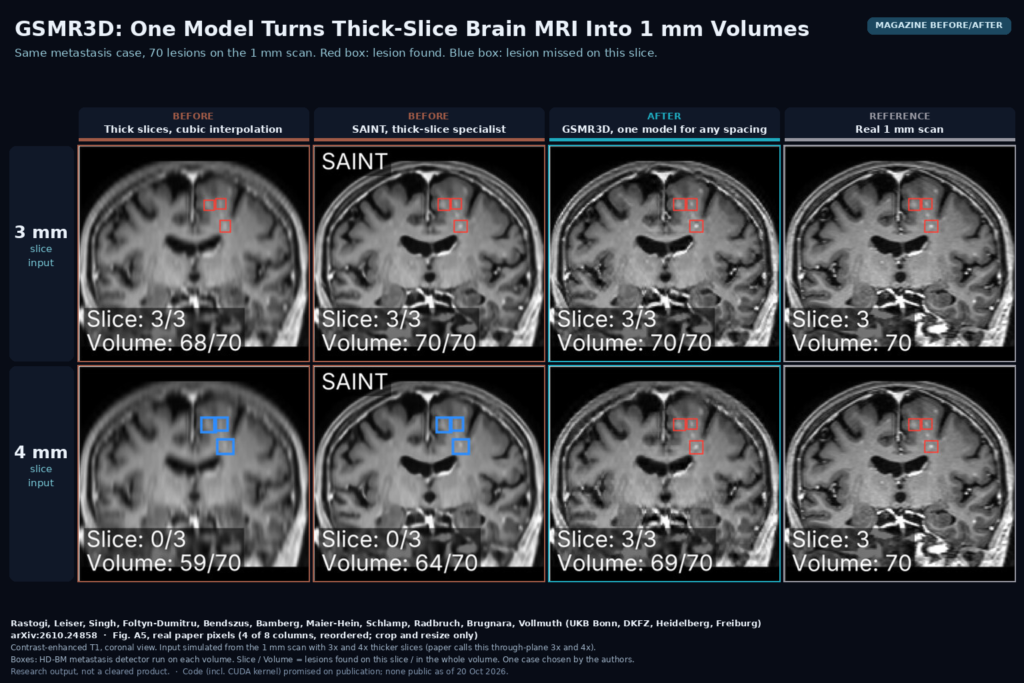
On classic image metrics the picture is mixed, and the authors say so. GSMR3D wins at isotropic 2x. For in-plane and thick-slice inputs, the geometry-specific specialists (LTE and SAINT) score 0.4 to 1.4 dB higher PSNR, while GSMR3D scores better on perceptual measures such as LPIPS and FID. To see which differences survive into clinical tools, the authors ran segmentation and detection models on every output. With the HD-BM metastasis detector run on the 1 mm scans as reference, GSMR3D kept 91.5% of lesions at 4x thicker slices, against 90.7% for SAINT and 86.1% for cubic interpolation. It also had the closest glioma segmentation agreement with the 1 mm scan at every geometry. A whole volume takes about 6 seconds on one A100, against roughly 140 seconds for the diffusion baseline they tested.
The figure
The featured image uses Fig. A5 from the appendix, one metastasis case with 70 lesions on the 1 mm scan, shown in the coronal plane. The paper shows eight columns; we kept four. Red boxes are lesions the HD-BM detector found and blue boxes are lesions it missed on that slice. In the top row the input had 3 mm slices. Cubic interpolation is soft but the three lesions on this slice are found, and both SAINT and GSMR3D find all 70 in the volume. The bottom row, with 4 mm slices, is where they separate. Cubic interpolation misses all three lesions on this slice and finds 59 of 70 in the volume, SAINT also misses all three on the slice and finds 64, and GSMR3D finds all three and 69 of 70. The authors chose this case as representative, so read it as an illustration of the cohort numbers above.
Limits
Every test input was simulated from a 1 mm scan with the same blur-and-subsample model the projection step assumes. A real 4 mm 2D acquisition has its own slice profile, can have gaps between slices, and brings its own noise and motion, and the authors state that prospective data are needed before anyone can say how the results transfer. That point weighs on the consistency step too, because it is only exact if the real acquisition matches the assumed degradation. The paper covers brain MRI only, T1 and contrast-enhanced T1 only, and factors up to 4x. Some reconstructions show faint block-like artefacts along the slice direction (Figs. A2 and A3). For brain parcellation with SynthSeg, the specialist and a plain residual CNN beat GSMR3D on thick slices, mostly in cortex, white matter, CSF and ventricles, so morphometry users should not assume the lesion results carry over. Even the best model at 4x still lost 57 of 670 metastases that the detector found on the 1 mm scans.
Code, data and license
As of 20 October 2026 there is no public code or weights. The paper says the training and inference code, including the fused CUDA kernel, will be released on publication, and a GitHub search for GSMR3D returns nothing yet. None of the training data can be downloaded. The CENTRIC, CORE and EORTC-26101 trial data and NAKO are access-controlled. The external test set, MR-RATE on Hugging Face, is gated and licensed CC BY-NC-SA 4.0, so it is fine for research evaluation and not for commercial training. The frozen first layer comes from NVIDIA’s MAISI autoencoder, so check the MAISI weight license as well once the code shows up.
How we would wire it into a viewer
We would run it as a job that writes a derived series next to the original. When a T1 or post-contrast T1 brain series arrives with slice spacing above some threshold, say 2 mm, the job converts it to a volume, runs the model to a 1 mm grid, maps intensities back to the original range, and writes a new series with a new Series Instance UID, Image Type DERIVED\SECONDARY, and a series description that says what happened, for example “T1 1 mm super-resolved (GSMR3D) from 4 mm”. The original series stays the primary one. In the viewer, the hanging protocol can offer the derived series for MPR and 3D, and a viewport banner should say the image is computed. Downstream tools such as a metastasis detector or tumour segmentation can take the derived series as input, with the source series referenced, so a radiologist can always go back to the acquired slices. For a pilot, we would acquire a few patients with both a thick and a thin protocol in the same session, because that is the only way to test the real-acquisition gap the authors flag. For background, see what a DICOM viewer does, our post on slice-aware restoration with ContiLNN, and our post on turning low-field brain MRI into 3T and 7T-like images.
Sources
- Rastogi, A., Leiser, R., Singh, P., Foltyn-Dumitru, M., Bendszus, M., Bamberg, F., Maier-Hein, K., Schlamp, K., Radbruch, A., Brugnara, G., Vollmuth, P. Arbitrary-Scale Anisotropic 3D MRI Super-Resolution with Gaussian Prototypes. arXiv:2610.24858, 2026. https://arxiv.org/abs/2610.24858. PDF: https://arxiv.org/pdf/2610.24858.
- External test data used in the paper: MR-RATE, Forithmus, Hugging Face (gated, CC BY-NC-SA 4.0), https://huggingface.co/datasets/Forithmus/MR-RATE.
- Featured image: Fig. A5 of arXiv:2610.24858, real paper pixels, four of eight columns, cropped, reordered and resized only.